Tough days at GitHub, a continuing series

It wasn’t even a week ago when I wrote about a major GitHub incident. Yesterday, they had another big incident, which lasted almost eight hours. There’s a public write-up already posted, which is surprisingly quick. While I’m personally very impatient to read these, I also know that it takes time to collect and synthesize the information you need to do a good job with them. I wish they had posted this as a preliminary write-up and then done a more detailed write-up in a couple of weeks. That being said, let’s look at the write-up!

Saturation strikes yet again

The immediate cause of the failure was network saturation on load balancers in Central US due to a new peak in traffic.

The failure mode is yet another example of saturation, a topic I’ve written about again and again on this blog. Heck, I even gave a talk on saturation a month ago.

Here’s the full paragraph on the failure mode:

The immediate cause of the failure was network saturation on load balancers in Central US due to a new peak in traffic. Originally this was caused by an Istio sidecar pod reaching its concurrency limits and failing to auto scale correctly because of a misconfigured policy that watched host service but not sidecar limits. One failure cascaded to more and eventually four HAProxy nodes exhausted their flow limits, degrading the gateway auth path and causing widespread authentication latency and failures. The problem was worsened by optimistic retry logic which overloaded internal load balancers.

Based on this, it sounds like the failure cascade looked like:

increase in external traffic → istio sidecars saturate (concurrency limits) → HAProxy nodes saturate (flow limits) → authentication requests fail

An increase in load on the system saturated one of the components (istio sidecar), and that propagated to another component (HAProxy), whose saturation broke the auth flow.

I wish they had included an architectural diagram here, that showed the relationship between the load balancers, the service that whose Istio sidecar pod saturated, the gateway, and the services that handle auth requests. Also, the wording gives the impression that only a single sidecar pod that saturated (an Istio sidecar pod), which would be surprising, but I’m also not confident that this is what the authors intended.

Diagnostic details: missing in action

The write-up doesn’t talk about the diagnostic work of the incident responders at all, which is a shame. I can’t tell from this write-up how difficult it was for them to figure out what was happening. There were auth failures, but it doesn’t sound like there was an increase in auth traffic per se, nor was the problem caused by recent changes to the auth system, which is where I would think to look first.

As somebody who was watching the updates to the status page as the incident was happening, I was struck by how they updates alternated between “we have identified the problem” and “we are experiencing issues:

Screen shot of some of the status page updates

I can imagine how frustrating it must have been for the responders to think they had found and fixed the problem, only to continue to see impact.

Retries made things worse

Retries are one of the tools in our toolbox to improve availability. And, usually, retries do improve availability! But retry logic also adds complexity to a system, and adding complexity to a system can introduce new failure modes. In this incident, retries hurt rather than helped, by increasing the load on an overloaded system.

The problem was worsened by optimistic retry logic which overloaded internal load balancers.

…

Residual Copilot authentication failures continued because client retry behavior amplified load: a failed token operation could generate many extra requests and enter a retry loop.

This is a great example of unexpected behavior of a subsystem whose primary purpose was to improve reliability from my conjecture on why reliable systems fail.

The Copilot Token Service sees 10X traffic

Note that there were two independent retry behaviors mentioned in the previous section:

  1. optimistic retry logic against the load balancers
  2. client retry logic against the Copilot Token Service

It turns out that the client retry logic was due to a previously undiscovered bug in Visual Studio Code(!), which led to one particular service (Copilot Token Service) taking longer to recover:

Delayed replies to a single internal endpoint triggered a latent retry bug in VS Code that amplified traffic by approximately 10x and caused delayed recovery for the Copilot Token Service.

…

Residual Copilot authentication failures continued because client retry behavior amplified load: a failed token operation could generate many extra requests and enter a retry loop. Copilot Token Service traffic increased from a normal 7–9K RPS to 70–100K RPS.

There’s no way you’re pushing out a VS Code bugfix to mitigate an incident! You’ve got to mitigate that on the server side, which is what the responders did, which brings us to the next section.

Mitigating the incident: multiple strategies

While the write-up doesn’t discuss diagnostic work, it does mention multiple mitigations that the responders undertook during the incident:

  • shifting traffic from the Central US region to the Northern Virginia region
  • paused HAProxy on the four saturated nodes
  • changed gateway retry logic (via PR)
  • blocked inbound Copilot Token Service token requests at the load balancer (returned 403s)
  • gradually ramping up blocked traffic

As responders, we are always limited in our ability to intervene based on the tools that we have at our immediate disposal. It’s incredibly useful to be able to do things like selectively block traffic, or dynamically change or even disable a reliability-related subsystem. Think about how difficult it would be to block specific types of requests during an incident in your organization, and to ramp that traffic back up slowly after the system recovers. Note how the responders had to use a pull request to change the behavior of the gateway retry logic. I wonder if the failure mode made this more difficult to carry out, but the write-up doesn’t say.

“Never again” means never preparing for a novel incident

The writeup ends, as most writeups do, with some action items intended to prevent recurrence.

To prevent recurrence, our follow-up actions include:

  • Correcting autoscaling policies to account for service-mesh sidecar concurrency and capacity.
  • Auditing Istio request, concurrency, and scaling limits across affected services.
  • Reviewing retry limits and backoff behavior across gateways and clients.
  • Addressing the VS Code retry behavior that amplified Copilot token traffic.
  • Improving load-balancer capacity monitoring and regional failover safeguards.

My eternal lament is that people spend too much of their focus on preventing the last incident from recurring. It’s not that I’m opposed to preventative work. It’s that I also want us to spend time on getting better at dealing with novel incidents. Engineering cycles are a finite resource, and every cycle spent on prevention is a cycle not spent on improving our ability to respond effectively to new incidents. And I promise you, you are going to face novel incidents in the future.

After all, I don’t think GitHub customers who experienced this outage take much solace in knowing that it was a different failure mode from the previous incident.
Quick thoughts on Azure Regional Outage from July 23, ’26

The folks at Microsoft Azure recently wrote up a post incident review for a networking issue in their West U.S region. From the included timeline, it looks like the impact was on the order of five hours. It’s a pretty short write-up, but let’s take a look at the contributors.

On 23 July 2026, a break-fix repair was initiated on an optical device to address a network reliability risk.

The first contributor mentioned in the write-up was work that was done to repair a device in their networking stack. Here I can’t help but think of the first bullet in my conjecture on why reliable systems fail. They made a change to the system in order to fix an ongoing problem, and due to a set of circumstances, things got worse rather than better.

A defect in our blast radius analysis system incorrectly expanded the scope of the repair event to include all optical devices egressing a specific datacenter. 

The second contributor mentioned was a (presumably) latent defect in their system. Note the irony of the failure mode here: I suspect this blast radius analysis system usually contributes to reliability, but in this case it hurt reliability by increasing the blast radius.

The safety validation step, which is designed to confirm that at least one of the two redundant datacenter paths remains available, ran but incorrectly concluded the operation was safe.

The third contributor mentioned was a safety check (good!) that passed even though the action was unsafe (bad!).

The checks validated each device individually rather than evaluating the aggregate effect of isolating all devices at once, a scenario that was not accounted for because the system was never designed to process a full datacenter’s worth of devices in a single request.

The reason it failed was due to an interaction with the second contributor: the blast radius being all of the optical devices egressing the datacenter. The designers never envisioned that the check would have to handle the sort of scenario that occurred as a result of the blast radius analysis system defect.

As a result, routes were withdrawn from multiple devices simultaneously, disrupting connectivity between the datacenter and the WAN – therefore impacting traffic entering or leaving the West US region.

It sounds like this change effectively disconnected the West US datacenter from the internet.

Once the route withdrawals took effect at 14:44 UTC, physical links and routing adjacencies continued to appear healthy, which initially masked the correlation between the break-fix activity and the connectivity disruption

Here we have our fourth contributor: the operators were receiving misleading signals from the system. The links and routes looked healthy, even though connectivity was broken.

The impact presented as a WAN routing anomaly, as third-party networks could not reach Azure in the region, rather than as a datacenter connectivity failure.

Our fifth contributor is another flavor of misleading signals. The symptoms presented as a routing issue between Azure and third-parties.

Although all physical work in the region was stopped, our engineers could not correlate to this recent change because the preparation activities in advance of the break-fix did not succeed, so the physical layer and traffic appeared healthy.

This is the sixth contributor mentioned in the writeup. The writing is a little oblique here, but I think what they are saying is that the repair event did not show up in their event log because the repair event didn’t actually complete. It sounds like the preparation activities were the ones that triggered the incident. But, because the repair event didn’t actually happen, the operators looking for events that correlate in time with the onset of the incident didn’t see the triggering event because it didn’t show up in the log of events. That’s my best guess, anyways.

Our automated recovery and rollback system detected the device failures, and attempted multiple retries to restore the affected devices. However, because that system depended on the same datacenter connectivity that had been disrupted, its automated rollback attempts were unsuccessful.

This is the seventh and final contributor mentioned. Azure has an automated recovery and rollback system (good!), but the failure mode in this case prevented automated rollback from succeeding (bad!).

As always, I’d love to know more about how the operators identified what the failure mode actually was, and how they traced it back to the optical device repair work.

GitHub has another tough day

On August 6, 2026, GitHub had a pretty rough incident: GitHub Actions was degraded for about nine hours. GitHub posted a public incident write-up. It’s only a few paragraphs long, but there are some interesting details in here.

This was yet another incident that involved saturation. In fact, the write-up even uses the word saturated when describing what happened.

The incident was triggered by a routine deployment to an internal Actions service responsible for processing events and generating Actions jobs. The deployment exposed an existing capacity and concurrency weakness. As pods were replaced during the deployment, remaining capacity became saturated, causing services to crash and triggering a cascading impact across multiple clusters and downstream services.

We often think of deployments as risky because we are changing the code that’s running in production, and the execution of that new code could trigger a behavior change in the system that could lead to an incident. But a deployment is itself also an operational change in the behavior of the system: our system behaves differently during a deployment than it does when nothing is being deployed. Ironically, this is one of the advantages of deploying more frequently: the more often we are deploying, the more that deployment becomes a normal part of the system behavior – we get more experience with the system in deploying state.

In this particular case, running in the deploying state reduces the number of pods available for doing work, as the older pods go online. In this scenario, it sounds like the system was running close enough to the margin that the reduction in capacity due to the deploy pushed the system over the edge, leading to a cascading failure. This is what the resilience folks call a brittle collapse, which is when the system fails in a non-graceful way when it reaches saturation.

As is common when recovering an overloaded the system, they got it back to healthy by shedding load (throttling) and by increasing capacity.

These services recovered at 17:00 after expanding capacity, throttling incoming webhook-triggered work to allow the system to recover, and increasing processing capacity for the backlog of affected events.

I wish the write-up had more details on what was involved in enabling throttling and getting that additional capacity to come online. In particular, I’m curious about whether this was easy to do or difficult. But, alas, you typically don’t get those kinds of details on public writeups.

And, of course, because every incident involves multiple contributing factors, there was a previously undiscovered bug that made things worse by consuming available capacity trying to run invalid jobs:

Due to a latent bug in one of the services responsible for job assignment, runners were getting assigned jobs that were no longer valid and then getting stuck retrying those jobs, preventing them from picking up valid work.

I would love to know more details about how the heck they figured out what was going on with these stuck jobs. I can just imagine being a responder to this incident, trying to get the backlog of work processed, and discovering that there are workers are blocked trying to execute invalid jobs! How did they figure out they were stuck? How did they figure out this was because of a bug?

They deployed a change to work around this problem, but I would love to know what kind of change that was. Was it a quick workaround to get things moving again? I bet it was, but we’ll never know…

This second stage of impact was mitigated by deploying changes to prevent runners from repeatedly attempting to acquire invalid jobs. These mitigations allowed the accumulated queues to drain and Actions to recover to normal operation.

The write-up ends with the typical “here’s what we’re doing to make sure this doesn’t happen again” text, but I am heartened by the last sentence (emphasis mine):

We are also making additional improvements to reduce the risk of cascading failures and accelerate recovery during large-scale Actions disruptions.

Too often, the focus of reliability work is entirely on prevention. I’m happy to see them also focus on preparing to recover more quickly. Because, as we all know, the next big incident is always just around the corner.

Synthesis is harder than analysis

Over the years, mathematicians, logicians and computer scientists have developed various calculi. If you have a background in computer science, you’ve likely heard of the lambda calculus, a model of computation that was developed by Alonzo Church. If databases are more your thing, then you’ve been exposed to the relational calculus without even knowing it, since SQL is based on the relational calculus. If you are into formal methods, then you’ve worked with the predicate calculus, better known as first-order logic. Finally, if you enjoy reading academic papers on programming languages, you’ve almost certainly run into the sequent calculus. However, when someone says “calculus” without modification (e.g., “I’m taking calculus next semester”), there’s no ambiguity about which calculus they are referring to: it’s always one particular calculus. Or, rather, two calculi that happen to be deeply related to each other: differential calculus and integral calculus.

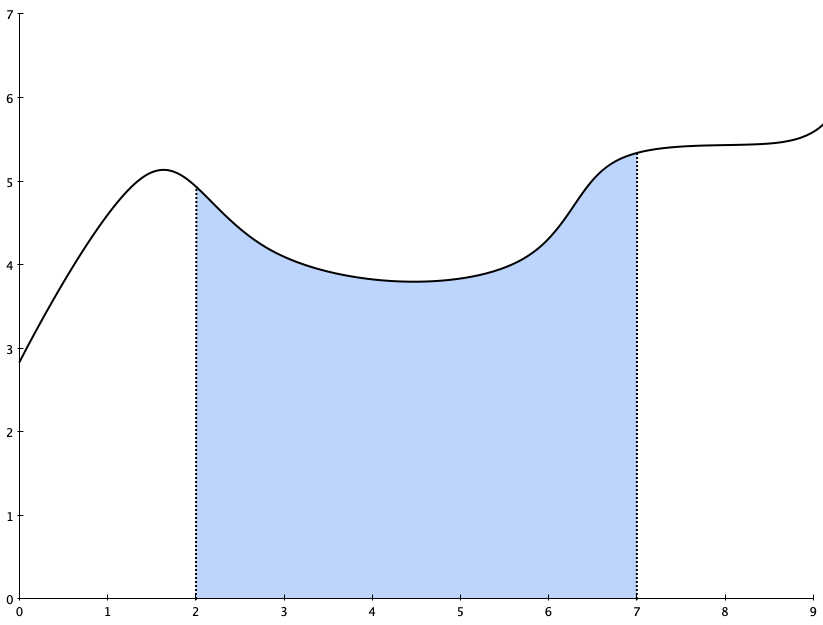
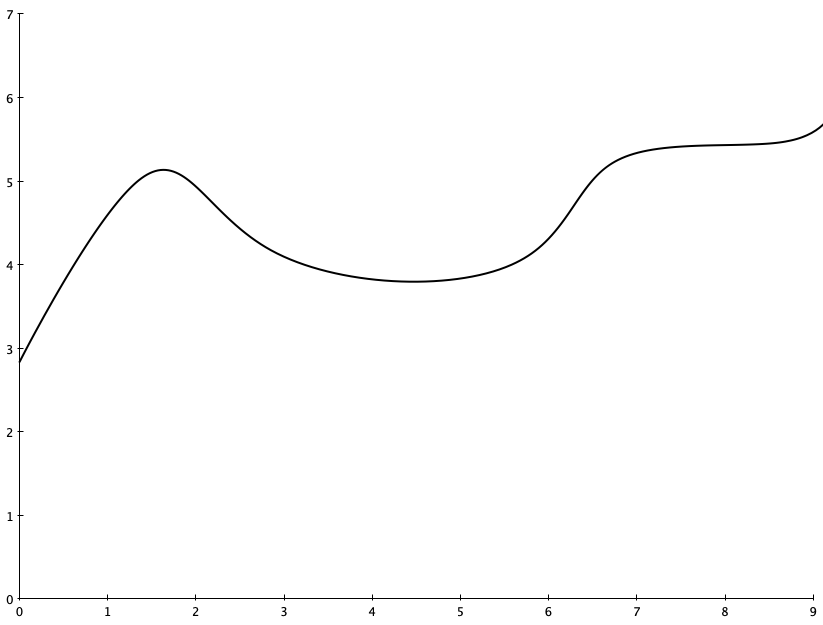
Visually, you can think of differential calculus as being about calculating the slope of a function at a given point. For example, consider this graph:

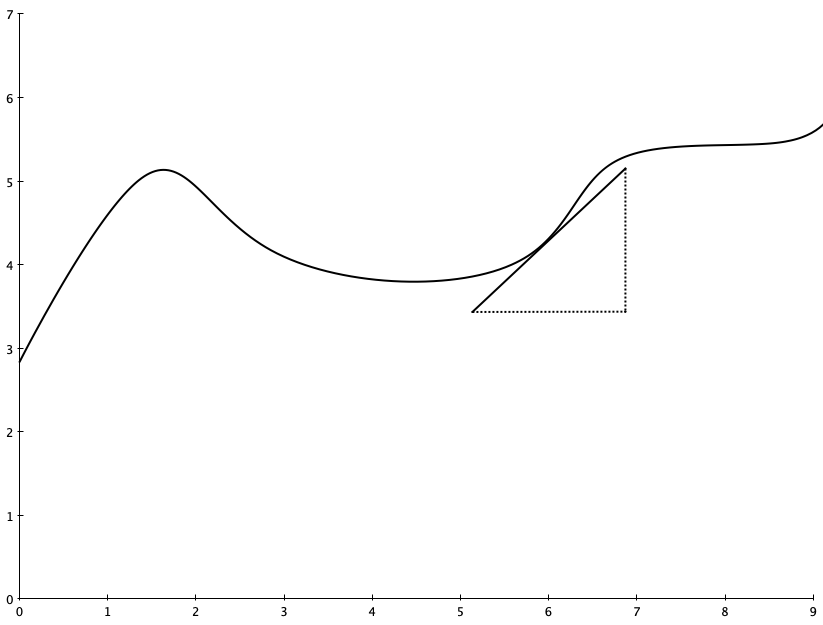
You might ask, “how quickly is this curve changing when x=6?” In other words, what is the slope of this function right in a neighborhood very close to x=6?

Differential calculus enables you to compute the slope of a function at a given point

Integral calculus, on the other hand, is about the area under the graph over a particular interval. For example, you might ask “what is the area under this curve between x=2 and x=7?

Integral calculus enables you to compute the area under a function over a given interval

If you study calculus, you’ll first be taught differential calculus (sometimes referred to “Calculus 1” or “Cal 1”) and then you’ll be taught integral calculus (“Cal 2”). When you study differential calculus, you learn the rules for calculating the derivative (slope-at-a-point) of a function. And it turns out that it’s quite straightforward to calculate a derivative, no matter what type of function it is. It’s just an algorithm, which means you can easily program a computer to compute derivatives if you wanted to. (As an aside, automatically computing derivatives is a fundamental element in the process of training LLMs. If you’re curious, look up automatic differentiation).

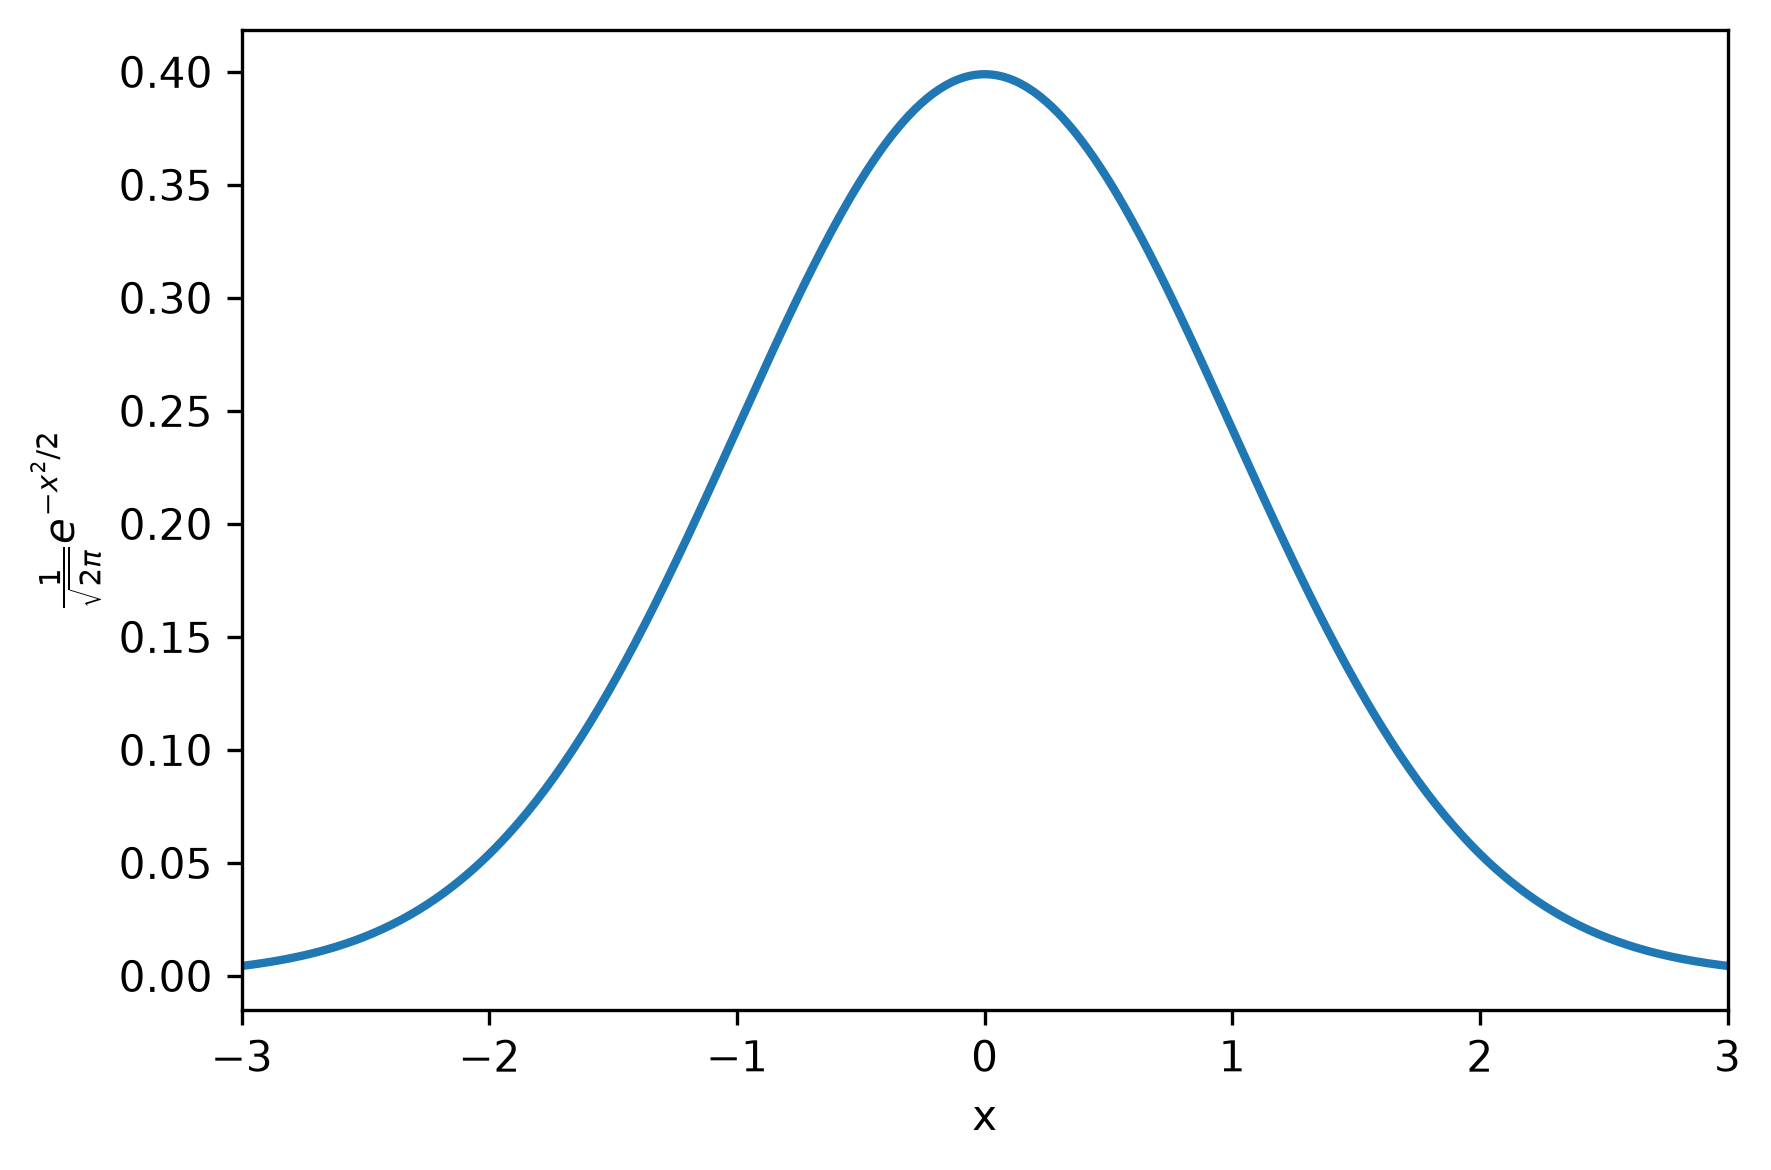
And then, you get to Cal 2, and you learn about how to compute an integral (area-under-a-curve). You will soon discover that, unlike in Cal 1, there is no algorithm for computing the integral of an arbitrary function. Instead, what you learn is a bag of tricks on how to compute integrals for different kinds of functions. You also learn that for some functions, there’s no closed-form solution at all for the integral! As an example, consider the Gaussian function, which shows up in the normal distribution. With zero mean and unit variance, it looks like this:

12πe−x22\frac{1}{\sqrt{2\pi}} e^{-\frac{x^2}{2}}
The infamous bell curve

Asking students to compute the derivative of this function would be a perfectly reasonable question on a Cal 1 final exam, the answer looks like this:

−x2πe−x22-\frac{x}{\sqrt{2\pi}}e^{-\frac{x^2}{2}}

But asking students to compute the integral of this function on a Cal 2 final exam would be unfair, because it’s not possible to do with the techniques they learned in class (at least, I didn’t learn the technique you’d need until Cal 3). Because the integral doesn’t have a closed-form solution, you need to express the solution as an infinite series, like:

12π∑n=0∞(−1)n2nn!(2n+1)x2n+1=12π(x−x36+x540−x7336+x93456−⋯)\frac{1}{\sqrt{2\pi}} \sum_{n=0}^{\infty} \frac{(-1)^n }{2^n n!(2n+1)}x^{2n+1} = \frac{1}{\sqrt{2\pi}} \left( x-\frac{x^3}{6}+\frac{x^5}{40}-\frac{x^7}{336}+\frac{x^9}{3456}-\cdots \right)

(Note: I asked AI for the integral of the Gaussian, I hope it got it right!)

It’s not obvious (at least, not to me) that differential calculus and integral calculus are related to each other. However, it turns out that these two calculi are opposite sides of the same coin, because integrals are anti-derivatives. That is, if f(x) is the derivative of F(x), then F(x) is the integral of f(x). This result is known as the Fundamental Theorem of Calculus.

This connection between differential and integral calculus raises an almost philosophical question: why is it so much easier to compute a derivative than it is to compute an integral? Back in 2011, somebody asked about this on the Mathematics Stack Exchange: Why is integration so much harder than differentiation? The top-voted answer was written by Qiaochu Yuan, and here’s the heart of it (emphasis mine):

Differentiation is a “local” operation: to compute the derivative of a function at a point you only have to know how it behaves in a neighborhood of that point. But integration is a “global” operation: to compute the definite integral of a function in an interval you have to know how it behaves on the entire interval (and to compute the indefinite integral you have to know how it behaves on all intervals). That is a lot of information to summarize. Generally, local things are much easier than global things.

In one sense, local things are easier than global things is a banal statement. Everybody knows that, for example, local optimization is much easier than global optimization. But it’s also a very deep one. And it gets at the title of this post, which is synthesis is harder than analysis.

I previously wrote about the difference between analysis and synthesis in the demon of the gaps. In analysis, we’re breaking a larger problem into smaller problems that separate out cleanly. These smaller problems are more localized, and hence easier to solve. This is why we advocate for principles like encapsulation and separation of concerns, to ensure our smaller problems are local.

The work of synthesis involves integrating(!) multiple things together. This pushes in the other direction: we are creating a problem that is less local. And global things are much harder than local things. The challenge we face is that some kinds of problems are just inherently synthesis problems. As I wrote in that previous post, incident response is one area where we are frequently confronted with synthesis problems: we have to understand how the pieces normally fit together in order to make sense of what is currently going wrong.

That’s why I think that this sort of synthesis work is important for SREs. Now, because synthesis is harder than analysis, and because SREs don’t have super-human cognitive abilities, it means that there is a limit to how deeply they will be able to understand any given component in the system. But the more they understand how the different components interact, the better positioned they are for helping resolve the tougher incidents.

Unfortunately, in our industry we haven’t recognized building up synthesis expertise as a first-class thing. That’s understandable because this work is very situated, it depends on the messy details of the particular system in the organization that an SRE works in. On the other hand, we can get better at learning how to learn about the operational details of a system. And that’s what I’d like to see more of.

I am dreading our LLM-written incident report future

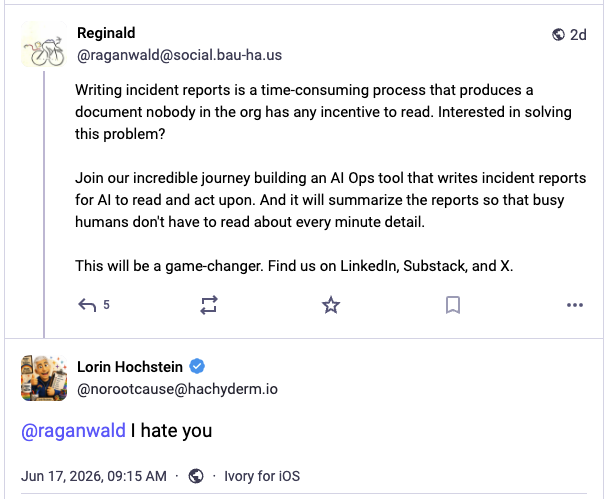
The other day, Reginald Braithwaite posted the following toot. For posterity, I’ve also included my own response to it:

Screenshot of a Mastodon toot by Reginald Braithwaite (@raganwald) and a response by Lorin Hochstein (@norootcause).

Reginald: Writing incident reports is a time-consuming process that produces a document nobody in the org has any incentive to read. Interested in solving this problem?

Join our incredibly journey building an AI Ops tool that writes incident reports for AI to read and act upon. And it will summarize the reports so that busy humans don't have to read about every minute detail.

This will be a game-changer. Find us on LinkedIn, Substack, and X.

Lorin: I hate you

Braithwaite’s post is dripping with sarcasm, but make no mistake, incident reports written entirely by LLMs is coming. And I am not looking forward to this future.

Before I dive in here, I want to note that there is a lot of toil you need to do in order to gather the data you need to write a good incident report, and LLMs can help significantly reduce that toil. I’ve got no issues there. But there’s a world of difference between using LLMs to help you assemble the ingredients involved in writing an incident report, and using an LLM to actually write the report itself.

Braithwaite’s post is horrifying to me precisely because of the seduction of the LLM as a tool for generating an incident report. After all, you can just ask it to write the report, and it’ll do it. And that’s exactly what scares me.

There’s a famous quote by the cartoonist Dick Guindon: “Writing is Nature’s way of showing you how sloppy your thinking is“. You might think you understand a concept, but it’s only when you put metaphorical pen to paper, when you actually try to explain the concept in written words to a potential reader, that you realize how fuzzy your understanding actually is. Writing in your own words forces you to confront how much you actually understand what it is that you’re writing about. Or, as Leslie Lamport put it, “If you’re thinking without writing, you only think you’re thinking.”

Having an LLM generate the text of an incident write-up bypasses this thinking step. Now there’s no human in the loop of the writing process that has to confront whether the explanation is actually consistent with the evidence that they’ve gathered. Instead, what you get is a plausible explanation of what happened to someone who is not intimately familiar with the details. They might read, nod along, and think, “yes, that makes sense.” But the LLM may have invented couplings between systems that aren’t there, and may miss critical interactions that were actually part of the incident, and because nobody did the hard work of actually synthesizing the data to do the write-up, nobody will notice. Because if you’re trying to reduce the writing effort, how much effort are you really going to put into checking the LLMs work.

In my view, LLM-generated incident write-ups are more dangerous than using LLM for coding or for AI SRE style tasks. For coding tasks, there’s always a testing step to check that the code exhibits the desired behavior, even if nobody looks at the code itself for meaningful details. For AI SRE tasks, either the LLM output helps you resolve the incident, or it doesn’t. In both cases, Nature is the ultimate arbiter of the LLM output.

But incident write-ups aren’t like that. The consequences of a poor report aren’t immediately apparent the way incorrect code or an incorrect operational diagnosis are in the moment. Instead, we get incident reports that have the superficially correct form, but are actually incorrect, with no obvious test for correctness.

And, because incident reports are time-consuming to write, the temptation to use AI tools to generate them will be overwhelming. But these LLMs will not go around talking to people that were involved in the incident. These reports will be simulacra; they will have the right form, but they will not provide readers with genuine insights into the nature of the system. The amount of learning will be significantly curtailed.

And, yes, people will probably use AI to summarize them as well.

It’s not a future I’m looking forward to.

Dear researchers column

The Journal of System and Software publishes a regular column called Dear Researchers: The perspective of software practitioners. Each column is an open letter to the software engineering research community from someone who works in tech. It’s edited by Austin Henley and Olaf Zimmermann, both of whom have experience in the two worlds of academia and industry.

They invited me to submit a column, which I did. When it finally gets published, you’ll be able to find it here: Dear researchers: help me deal with incidents! The published version will eventually go behind the journal’s paywall, but here’s a preprint of the column that you can always read free of charge.

The demon of the gaps

Mephistopheles (a medieval demon from German folklore) flying over Wittenberg, in a lithograph by Eugène Delacroix.

Modern software systems contain within them a mind-boggling level of complexity. As software engineers, we make this complexity manageable through techniques like decomposition, information hiding, and abstraction. We endeavor to break our systems up into components that interact over well-defined interfaces. By doing this, the surface exposed to individual software engineers is dramatically reduced: no individual has to understand how the entire complex system works in order to contribute to their system. Instead, each software engineer needs to understand only the individual component that they work on, along with the interfaces of the other components that they interact with. Decomposition is synonymous with analysis, where you study a larger thing by breaking it up into smaller pieces that are more amenable to understanding.

You can see this strategy of complexity management in action in microservice architectures. An engineer needs to understand the service that their team owns, and the interfaces of the services that their team calls out to. This architecture effectively bounds the information that an engineer needs in order to work effectively. Microservice architectures aren’t there for scaling the software itself, they’re there for scaling the software organization.

Unfortunately, when the system breaks down, this complexity management strategy breaks down itself. Just as hurricanes don’t respect political boundaries, system failures don’t respect component boundaries. Yes, sometimes the problem in a software system is limited to the failure of a single component. Those are the easiest cases to diagnose and mitigate. However, the hairy incidents are the ones that arise due to unexpected interactions across components. Maybe you have several services that are throwing errors, or maybe none of the services are throwing errors but customers are still seeing incorrect behavior. There’s no obvious change that correlates with the start of impact, or maybe you don’t even know when the impact started because the customer impact isn’t reflected in your existing metrics.

When you’re in the throes of an incident that involves an unexpected interaction, this architecture that was built for managing complexity now works against you. Because you’ve built an analysis solution but you’re now faced with a synthesis problem. You need to understand how the pieces all normally fit together to function in order to determine what is going wrong with the system right now. You’ve optimized to avoid requiring anybody to understand how the whole thing works, but now the whole thing isn’t working, and no one person knows how the whole thing works.

The job of the incident responders is to collectively figure out how to do that synthesis. You’ve brought together a group of people who each understand the functions of different components of the system, and you need to work together to build enough of an understanding of how the system functions to debug what’s going wrong. As an ad hoc team, the incident responders have to move up and down the abstraction hierarchy to figure this out.

This sort of in-the-moment reconstruction of system function from component parts is an essential part of incident response for the most complex incidents, but it’s rarely treated as first-class work that’s worthy of study and support. The recent book Crisis Engineering by Marina Nitze, Matthew Weaver, and Mikey Dickerson is the exception that proves the rule: they do discuss the work of building a model of the system during a crisis to help figure out what’s gone wrong. But I struggle to recall any other guidance I’ve read about incident response that talks about how to prepare for doing this sort of work. It’s important work, and it’s difficult, and the ability to do it well can have a huge impact on the time it takes to mitigate the hardest incidents. This is stuff that even the best individual humans struggle with, because it involves a group of humans working together effectively, with each person having a partial model of the system. And if the best humans struggle with it, I don’t think AI SRE tools are going to save us here: if the best humans struggle, the AIs will too. We need to figure out how to get better at this collectively. Like so many things, it’s a coordination problem.

Reliability as a game of improving the odds

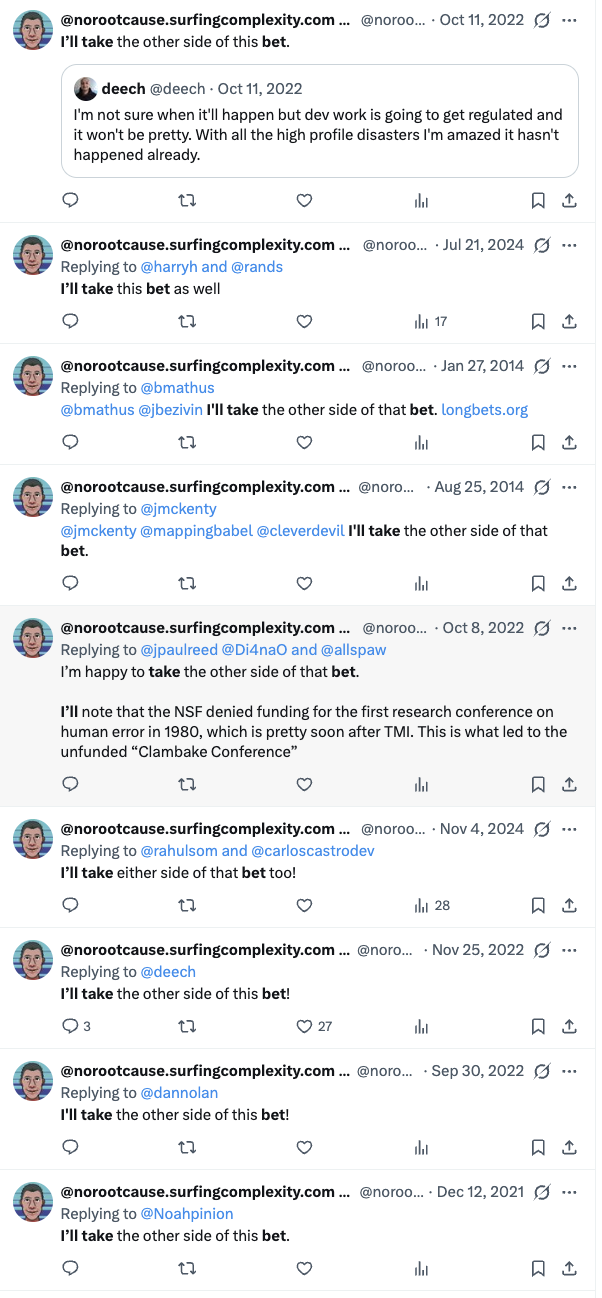
I’m a betting man; I just enjoy making bets, even when there are no stakes at all.

Examples of my enjoyment of betting

And when you talk about bets, you end up talking about odds.

It turns out that reliability is also about odds, even though we don’t use the language of odds in our domain. Consider how we talk about availability. We report system availability as a number of nines: for example, we might say “four nines of availability”, which means 99.99% of somethings are good over some time interval. The canonical example of those somethings are successful requests. In that case, if someone says a service has four nines of availability over the past three months, that means that 99.99% of requests succeeded over that time period. We could express the same information by saying that there is a one in ten-thousand chance that any given request failed in the past three months.

If your system has exhibited four nines of availability in the past three months, and you assume that the availability of your system in the near future will be like the availability of the past (a dangerous and unwarranted assumption, but let’s go with it for a moment), then we could also express this information using the language of odds, by stating that the odds of a request failing are ten-thousand to one.

But this isn’t a post about describing availability in the language of odds. Instead, what I want to talk about is how all reliability work is inherently about improving the odds, increasing the likelihood that the system stays up. Any time we build any sort of reliability mechanism, be it load shedding, autoscaling, canarying, staged deployments, automated rollbacks, or what have you, we are building automation into the system that either eliminates or reduces the impact a subset of potential problems. If you ask an engineer working on improving reliability, “will this prevent all future incidents”, they will tell you “no, of course not”.

However, we don’t explicitly think of reliability work in terms of improving the odds. Instead, we tend to think of it as deterministically addressing a specific class of problem. You’ll hear questions like, “how many historical incidents would this tech have prevented?” in trying to determine whether engineering should invest in a particular reliability solution. They are looking for an answer like, “this would have prevented 20% of our SEV1s and SEV0s”. This 20% isn’t interpreted as a likelihood, instead it’s used as an estimate of impact, as in “this will improve our availability by around 20%”. The idea is that this reliability work will deterministically eliminate or mitigate a certain fraction of incidents; we just don’t know exactly what that fraction is, so we estimate it from historical data.

What I would like to propose in this post is that we think about all of the various kinds of reliability work as improving the odds of our system being up longer, instead of assuming that reliability work will have a fixed effect, and try to estimate the effect size. I’ve got two motivations for taking this perspective of reliability work as odds improvement.

The first motivation is that I don’t think we can ever estimate the effect size without error bars that are so huge that the estimates are themselves meaningless. As I’ve written about previously, the variation in incidents is just too large relative to the amount of data we have available. And, to make the estimation problem from historical data even worse, our system is changing over time. Or, to put it in technical terms, I don’t believe that incidents can be modeled as a stationary process. (Heck, if they were stationary, then that means that reliability work could not have an impact, because then the process would change over time!). Note that I’ve never seen anybody try to validate the estimates, they’re always point-in-time estimates used to justify work, and then promptly forgotten about. In one sense, that’s fine, they served their purpose of convincing leadership that we should allocate cycles for a particular kind of reliability work. But we shouldn’t fool ourselves into believing that these estimates are meaningful: they’re for persuasion, not insight.

It’s my second motivation, though, that prompted me to write this blog post. And that’s because the idea of reliability work as improving the odds of effectively mitigating future incidents is a useful framework for thinking about work that improves resilience. I’m interested in improving the skills of the people who respond to incidents, putting them in a better position to deal with those future unforeseen, surprising scenarios. One way to do this is learning from how responders dealt with previous incidents, the different sorts of observability data they had access to and how, the different knobs that were able to turn, and so on. While the next incidents will be different, the set of tools that are available during incident response are generally the same. There’s no way I can give a quantitative of estimate how this sort of skill improvement work will impact reliability. And despite the enormous number of random factors, I am confident that it will improve our odds.

Flipping the bozo bit on flips the learning off

I’m too young to have seen Bozo the Clown myself, but I’m old enough to get the references

“Flipping the bozo bit” is an expression from the software world. Think about a time when you reached a point where you simply stopped respecting the opinion of a particular person, most likely a co-worker. From that point on, you disregarded what they said. This is what flipping the bozo bit is. This person isn’t worth listening to, they’re a bozo.

There’s a related phenomenon, where we hear an anecdote about some bad outcome that happened to someone else, and our conclusion is that this outcome occurred because, well, that person is a bozo. I’m writing, of course, about incidents. You’ve seen this happen, right? An incident happens, the details of the incident get passed around, and somebody makes a comment like, “how could they have [not] done X?” The subtext is “what a bunch of bozos!”

This is on my mind because of the latest AI-related incident that befell PocketOS. You can read about it in the Twitter post written by the PocketOS founder, Jer Crane. The post is titled An AI Agent Just Destroyed Our Production Data. It Confessed in Writing. Unsurprisingly, this post got a lot of online attention. I saw a lot of “wow, was this guy ever a bozo” reactions to this story. I want to talk about why this reaction is counter-productive. I also want to call out the technical term for this phenomenon, which is a cousin of flipping the bozo bit. It’s called distancing through differencing.

The term distancing through differencing was introduced by the American resilience engineering researchers Richard Cook and David Woods in their 2006 paper: Distancing Through Differencing: An Obstacle to Organizational Learning Following Accidents. Technically, it’s a book chapter, from Resilience Engineering: Concepts and Precepts. It’s very readable, and I recommend it. All of the quoted text below is from that paper.

By focusing on the differences, they see no lessons for their own operation and practices.

When people hear about an incident and respond by concluding “an incident like that would never happen to us; that happened to those workers over there because they are clearly not as careful as we are, that’s distancing through differencing in action.

Overall they decided the incident “couldn’t happen here”.

The Cook and Woods paper illustrates the phenomenon with a case study of a chemical fire that broke out at an American manufacturing plant. There had been a similar fire that had occurred previously at the same company, at an overseas plant. The American employees knew about the previous fire, but they had concluded that there was nothing to learn from that other fire, as that sort of accident couldn’t happen to them in the U.S. After all, those overseas workers were less skilled, less motivated, and less careful. In short, those overseas workers were perceived as different.

Ironically, after the chemical fire at the Ameircan plant, other workers at that very same plant also exhibited distancing through differencing.

Workers in the same plant, working in the same area in which the fire occurred but on a different shift, attributed the fire to lower skills of the workers on the other shift.

Cook and Woods note that our tendency to focus on differences between us and them when the incident happens to them leads us to miss aspects of the system that we actually have in common with them. By focusing on the differences, we miss the opportunity to learn from their experiences, because it seduces us into believing there’s nothing for us to learn here.

do not discard other events because they appear on the surface to be dissimilar. At some level of analysis, all events are unique; while at other levels of analysis, they reveal common patterns.

Now let’s circle back to the PocketOS AI-related incident. If we come to the conclusion that PocketOS employees were simply using AI irresponsibly, and that we are more responsible than that, we learn nothing from the experience. I was heartened to see that Railway, the vendor used by PocketOS that exposed the delete API, has made changes to the overall system to improve safety; see their post: Your AI wants to nuke your database. Guardrails fix that.

Stepping back, this isn’t the last AI-related incident we’re going to see in our industry, not by a long shot. The next time you read one of those, if your reaction is “they should have known not to do X”, then you’ve fallen into the distancing through differencing trap.

(As an aside, “they should have known…” is an incoherent sentence. It’s one thing if somebody deliberately took on excessive risk. But it’s another thing if they unknowingly took on excessive risk. How can you blame a person for not knowing something?)

When this process of learning moved past the obstacle of distancing through differencing in this case, the organizational response changed.

After all, there but for the grace of God go we all.

How incidents can teach us about what’s already working well

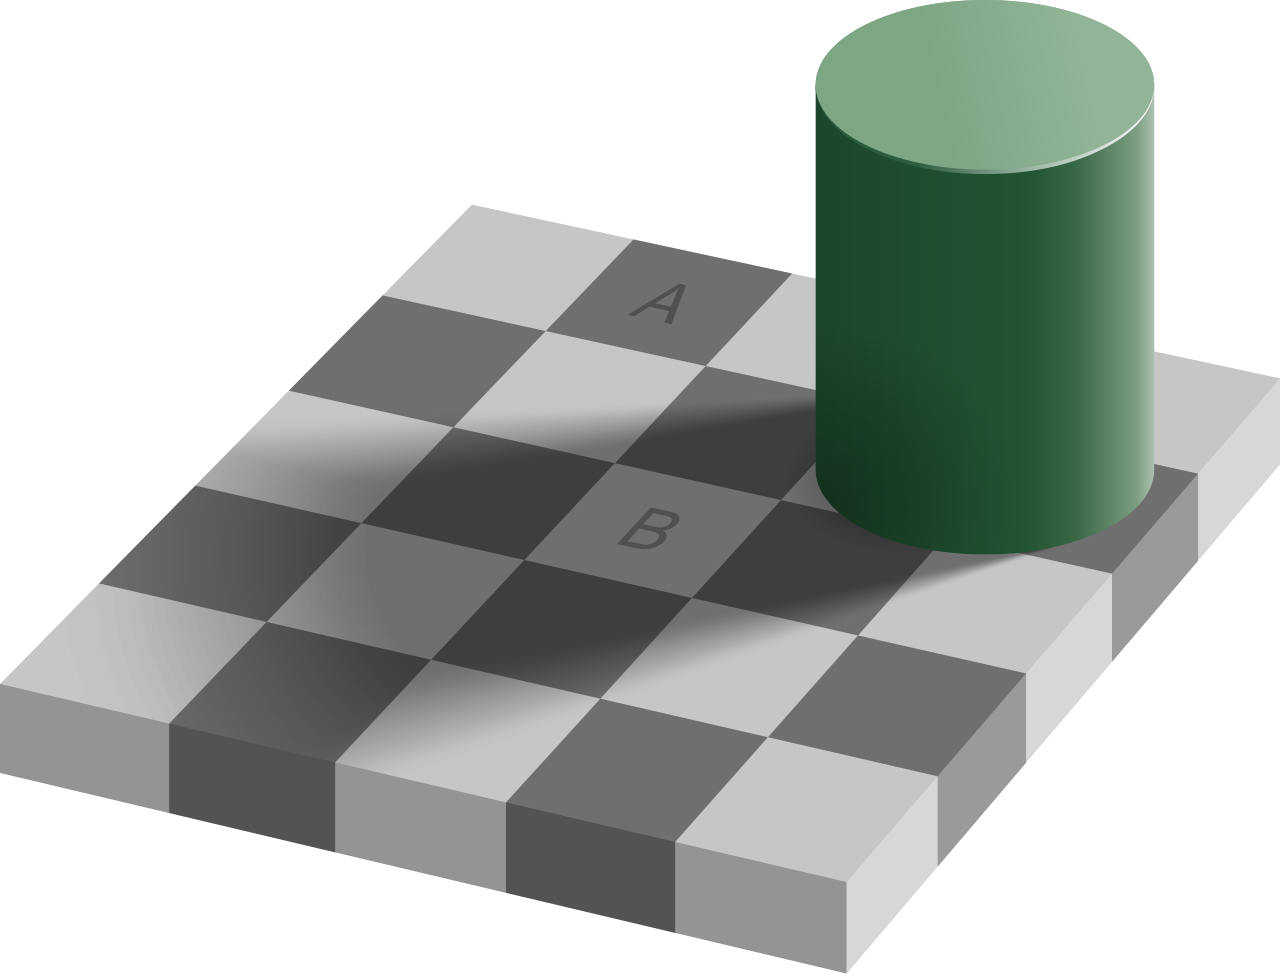
Here’s a famous optical illusion, which was developed by the American neuroscientist Edward H. Adelson.

Source

Even though square A appears darker than square B, the two are, in fact, the exact same shade of gray. It’s such a powerful illusion that, even knowing the illusion doesn’t destroy its effect; you’ll still “see” the illusion after you know about it. It’s so powerful that you may not believe me over your lying eyes. If you’re on macOS, you can confirm the illusion by opening the Digital Color Meter app and hovering your mouse pointer over each square in turn. You’ll see that both squares have the same RGB value. In hex, the value is #646464.

I’m going to suggest two stylized reactions to witnessing this illusion. One reaction is to say, “Oh, no! This illusion clearly illustrates a flaw in the human visual system! We should work on developing a vision correction technology so that people don’t fall victim to problems that would arise from this failure mode in human visual processing.”

A very different reaction is to say, “Oh, wow! This illusion gives us a hint into how the human visual system functions! Our brain must contain a prior model about the relationship between light, shadow, and objects, and is imposing that model when processing the signals coming from our optic nerve. This illusion appears to be an example of a pathological case which violates the human brain’s model.”

The first reaction is, admittedly, a ridiculous strawman. These sorts of illusions are harmless, so there’s no motivation to try to “correct” from them. After all, it’s no coincidence that the illusion was developed by a researcher who studies human vision. Even though our visual system is failing us in this strange case, the value of an illusion like this is not to learn the circumstances in which our vision fails, but instead to use the failure to gain insight into how our vision works so effectively for the vast majority of the time.

Last week, I wrote a post about Safety-II, the idea that we will learn more about how to create reliability in our system by studying the (common) successful cases rather than the (rare) failure cases. But we can also use the failure cases to learn about how the system normally succeeds! Just as neuroscientists can use optical illusions (where the vision system fails) to learn how the visual system succeeds, we can use incidents (when our system fails) to learn about how our system succeeds.

To make this more concrete, imagine you’re in an incident review meeting, and one of the incident responders, someone who is a real expert at your company, is talking about how, in hindsight, they misdiagnosed the problem during the incident. The signals that they saw misled them until thinking that the system was in state A, when really the system was in state B. And that led to the incident taking much longer to resolve, because the responders went down the wrong path.

The typical sort of question to ask in a review meeting would be along the lines of “what can we do to make sure we don’t misdiagnose this type of problem in the future?” But, there’s a very different question that you ask. And that question is, “how did the responder come to the conclusion the system was in state A?” Asking this question will expose details about the responder’s mental model of how the system actually works. If the responder was an expert, and they were led astray by the signals, then it’s likely that this incident was a pathological case, an operational equivalent of the optical illusion we saw above. By asking the responder about how they made the diagnosis, you are giving the meeting attendees the opportunity to learn from the expert responder. Similarly, you can ask the responder, “how did you finally figure out that the system was in state B?”, which will give you another chance to retroactively witness the work of an expert in action.

Like optical illusions, incidents are pathological cases. But, unlike illusion, incidents aren’t harmless. This means that the natural reaction is, “what went wrong here, and how do we stop doing that?” But if our goal is improvement, we should recognize there’s a lot more leverage in maximizing the opportunity to learn about what’s working well today, from the experts who are doing that work well. After all, there’s a reason we called that responder an expert; their work had led to a lot more success than failure.